
Head Pounding in Your 50s? The Hidden Truth Behind Menopausal Headaches

In Your 50s, Does Your Heart Pound in Your Head? The Hidden Face of Menopausal Headaches
|
"I used to get migraines occasionally when I was younger, but they've started again now that menopause is approaching. They're much worse than before, and it feels like my heart is pounding in my head." |
As they enter their 50s, many women experience headaches with different patterns than before. In particular, throbbing headaches, often described as 'my head is pounding,' are unwelcome guests that disrupt daily life. Many attribute this to aging or stress, but in fact, it could be a signal from the dramatic hormonal changes in our bodies.
|
[CASE] Ms. L, 52, was consulting with an OB/GYN for menopausal symptoms. Her primary concern was throbbing headaches that accompanied sudden hot flashes. "Even while sleeping, my face would suddenly flush, my heart would pound, and then, without fail, my head would throb with pain." If headaches appear as part of a set with other menopausal symptoms like this, we should suspect a common underlying cause. |
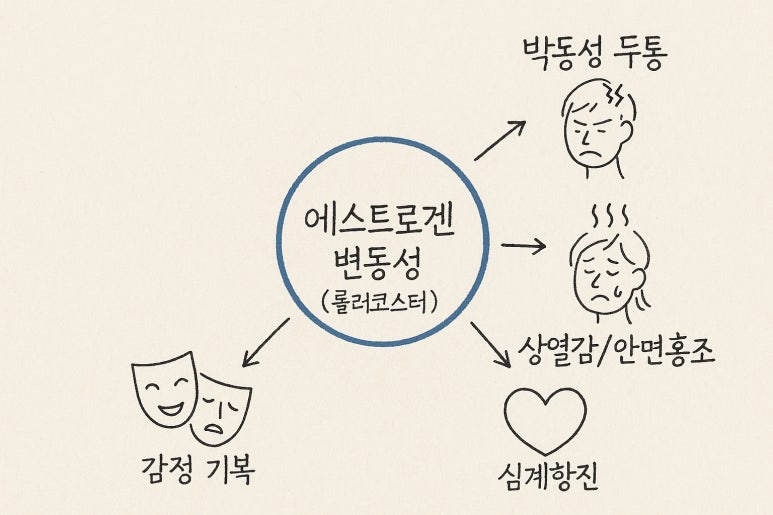
The culprit is the 'estrogen rollercoaster.' Many cases of 'headaches in women in their 50s' fall into this category. The menopausal transition (perimenopause) is not simply a period where the female hormone estrogen gradually decreases.
Rather, it's more like a 'period of hormonal upheaval,' where levels unpredictably surge and plummet repeatedly, like a final blaze. It is precisely this 'sudden drop in estrogen' that shakes up the brain's pain regulation system.
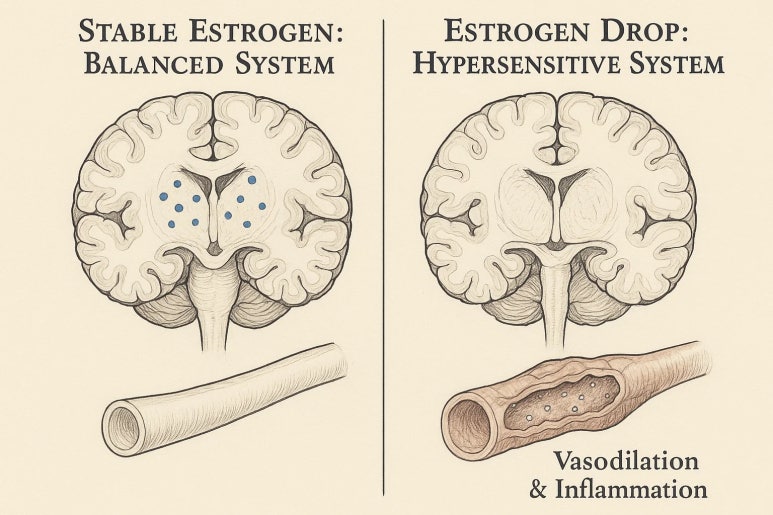
Estrogen plays a crucial role in maintaining the balance of neurotransmitters in the brain, such as serotonin and CGRP (calcitonin gene-related peptide). When estrogen levels fluctuate, the brain's pain regulation system loses its direction, and cerebral blood vessels easily become hypersensitive to even small stimuli.
This is why 'menopausal migraines' often present as throbbing headaches.
Sudden drop in estrogen levels → Neurotransmitter imbalance in the brain → Increased cerebrovascular hypersensitivity → Exposure to triggers (e.g., stress) → Vasodilation and inflammation → Onset of throbbing headache.
|
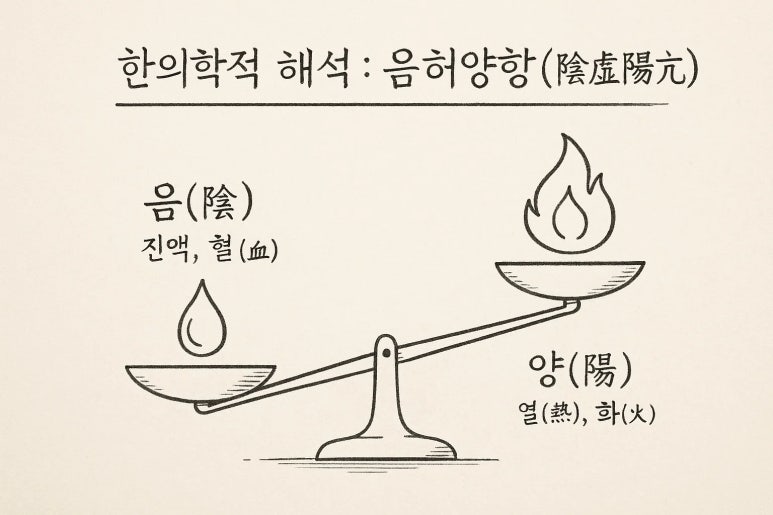
[REFERENCE: TRADITIONAL KOREAN MEDICINE PERSPECTIVE] In Traditional Korean Medicine, this state is explained as 'Yin Deficiency with Hyperactivity of Yang (陰虛陽亢)'. As the Yin energy (similar to estrogen's stabilizing function), such as the body's fluids and blood, becomes deficient, the relatively Yang energy—heat and active energy—surges upwards, causing hot flashes, palpitations, and headaches in the head and face. The method for 'reducing hot flashes' is ultimately the process of restoring this disrupted Yin-Yang balance. |
|
[OTHER POSSIBILITIES] Of course, not all throbbing headaches are due to menopause. If blood pressure remains consistently high even in a stable state, hypertensive headaches should be suspected, and an internal medicine consultation is necessary. |
|
[A SHIFT IN PERSPECTIVE] However, if your throbbing headaches come with hot flashes or mood swings, this could be your body's signal that you've entered a new stage: menopause. During this time, it's important to understand 'female hormone management' and, if necessary, explore professional treatment options such as Hormone Replacement Therapy (HRT). This is because managing 'estrogen deficiency symptoms' is not just pruning the branch of headaches, but rather tending to the root of the tree. |


